Showing posts with label sports therapy. Show all posts

Tuesday, 20 January 2015

Glute Activation: Reduce risk of injury and increase performance

Hello again. This article follows on from previous articles on foam rolling and mobility, flexibility and stability. These three areas have been discussed as part of a pre-training routine, in order to reduce risk of injury and enhance performance.

This article will look at what glute activation is, how it can be achieved and why should it be considered as part of your pre training routine.

What is glute activation?
Your glutes are a powerful muscle group, made up of the gluteus maximus, gluteus minimus and gluteus medius.  These muscles play an integral role in your performance, as they are heavily involved in powerful movement such as sprinting, jumping or change of direction.

If these muscles are weak or inactivate (gluteal amnesia), other muscles are forced to compensate, leading to an increased risk of injury and decrement in performance levels. Therefore it is important to strengthen these muscles and ensure they are ‘active’ ahead of exercise.

How can this be achieved?
There are a number of stretches and exercises we can do in order to activate our glutes.

Pre-activating muscles with near maximal exercises / lifts have previously proved effective, through enhancing neural drive. A disadvantage of this is that muscles are exposed to a risk of fatigue and you must have access to gym equipment.

By activating muscles using body weight exercises, your routine can be done anywhere and anytime, with no equipment required.  For example this can be done on the pitch before a game, as a part of your pre match warm up. Mini bands can be used to add an external resistance to the body. These bands are not too hard to find and won’t break the bank either.

Here are a few examples. Try to ensure all exercises are performed in a controlled manner.


Glute Bridges (double / single leg)


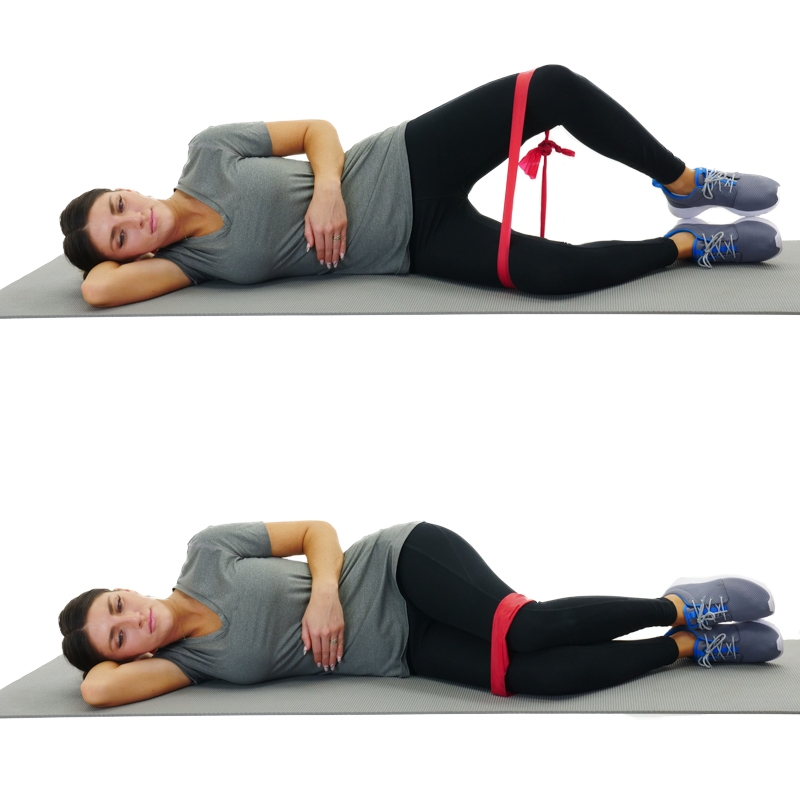
Clams


Hip Abductions


‘Fire Hydrant’


‘Donkey Kick’


Side Steps


Monster Walk


What does the research say?

A study by Crow et al. (2012), examined the effect a low load warm up, to activate the gluteal muscles, had on performance with a group of Australian rugby players.

Seven exercises were used in the warm up to target the gluteus, including some of the exercises listed above; glute bridges, clams and hip abductions.

Results of the study showed that this warm up significantly increased lower body peak power and improved jump height scores in a weighted (20kg bar) squat jump test.

These results highlight that a warm up incorporating gluteal activation exercises has the ability to increase performance levels significantly.

So why not give it a go your self?

If you would like any tips on the exercises listed above or any other details regarding glute activation, as always, I am more than willing to help.

Thank you again for taking the time to read this article! Goodbye for now.

Reference

Crow, J., Buttifant, D., Kearny, S. and Hrysomallis, C. (2012). Low Load Exercises Targeting the Gluteal Muscle Group Acutely Enhance Explosive Power Output in Elite Athletes. Journal of Strength and Conditioning Research, 26(2), pp.438-442.

Thursday, 15 January 2015

Massage and Self-Myofascial Release


Welcome back to the recovery series. This is now part 3, and our subjects for discussion are massage and self-myofascial release (SMR).

Now, I imagine most people understand the basic premise of what a massage is and what it consists of. Usually there are two types, a regular massage which is more therapeutic and relaxing using softer contact, and also sports massage which is a more physical experience getting deeper into the muscle to release tension, knots, and bound up tissue caused by exercise or general life1.


This leads to a happy customer either way in most cases (not the kind of happy endings you may be thinking … this is a child friendly article after all) as the tension of muscles can be released leading to greater range of movement, and can also assist stress management2.

SMR is slightly different. A lot of you reading this will have heard of it, and if you haven’t, I’m hoping that you have heard of something called Foam Rolling. They are one and the same in that SMR is what it says – releasing the tension of the fascia by yourself. Broken down this is; self - you, myofascial - the thin layer of fascia that covers the muscle belly, and release – how can I put this … “to free from confinement/to free from anything that constrains”3. Yes I did just use a dictionary for that, don’t judge me.
Essentially it is just using a foam roller, or other such tools, to release any areas of tension in the body4.


There are pros and cons to both of these in my opinion. With massage you can get a more thorough treatment on any identified area, but unless you have a friend in the business who can give you a good deal it can often be quite pricey. Especially seeing as the effects are not life long but only short term5.

It can also be a bit less time effective, as depending on your masseuse it could be either 30 or 60 minutes per treatment, plus travel time to and from. Plus there’s one more, you might not know when you’re going to be in need of a massage. So unless you have a regular booking already in place, if something causes you to need one – you may then have to wait for an available slot.

With foam rolling the only expense is the initial purchase of the items. This can be entirely based upon your budget or needs. For me – I use a Trigger Point roller; it’s quite heavy duty and has ridges allowing for a more thorough release. It’s a little more expensive than some, but I’ve had it for almost 3 years and it’s still holding strong. I used to own one of the simple and cheap rollers, but being 115kg+ at the time, I flattened it within a few weeks of regular use. I also use a massage stick to roll my calves and quads, and a lacrosse ball, hockey ball or sometimes even a golf ball (for the real sneaky little knots hiding away) to get at individual knots rather than a whole muscle belly. I’m not saying you need all these, but it’s just what I use.

Apart from that, with foam rolling all you need is the know-how (knowing where is sore and how to roll that area – check out reference 4 & 6 for more info), and some floor space to do it. Time-wise I feel it is more efficient as a little and often approach can alleviate a lot of issues.


What role do these both play on recovery I hear you ask (and even if you’re not asking, I’m going to say anyway); both can be used to alleviate muscle fascia tension, which will allow a greater range of movement. It can also help to reduce the amount of waste product build up in the area, with appropriate technique (generally considered to be towards the heart) helping to flush waste.

You can buy Foam Rollers here at pretty low cost. Much cheaper than paying a sports therapist to give you a massage... (And less painful!!)

Once again, I hope this article was helpful for you. If it was, please give it a share on social media. There are plenty of other good articles to read on the Macro Man blog, so check them out and get anyone you think might be interested to have a look.

The Recovery Series is well under way, with 3 parts now complete. Next week we’ll take a look into active recovery and how it could help you.

Thanks for reading,


References

1.     Cherkin, D.C., Sherman, K.J., Kahn, J. et al. (2011). A comparison of the effects of 2 types of massage and usual care on chronic low back pain: a randomized, controlled trial. Annals of Internal Medicine, 155(1).
2.     Sherman, K.J., Ludman, E.J., Cook, A.J. et al. (2010). Effectiveness of therapeutic massage for generalized anxiety disorder: a randomized controlled trial. Depression and Anxiety, 27(5).
3.     http://dictionary.reference.com/browse/release?s=t
4.     Robertson, M. (2008). Self-Myosfascial Release: Purpose, Methods & Techniques. Robertson Training Systems, Indianapolis, USA.
5.     Furlan, A.D., Imamura, M., Dryden, T. et al. (2008) Massage for low-back pain. Cochrane Database of Systematic Reviews, 4(1).
6.     http://www.lightfield.com/etc/Self_Myofascial_ReleaseMM.pdf - accessed 11/01/2015

Friday, 19 December 2014

Foam Rolling - How to do it, why you should do it and who says it's worth it


This article is all about the world of self-myofascial release (SMR), in particular, foam rolling.  If you have never heard of this term or would just like to know a bit more information about it, you have come to the right place! This article will be discussing what a foam roller actually is, why they are used, what they actually do and, finally, what does the latest research say about them?

I hope you enjoy!


What is a foam roller?


So first up, what is a foam roller? Its not a trick question, a foam roller is simply just a cylinder piece of foam (that rolls).  They come in various sizes and densities, which is usually indicated by the colour of foam. White rollers are the softest, black rollers are the firmest and blue rollers are somewhere in between. They are not hard to find either, just search online for a foam roller and you are sure to find a stockiest.


For anybody that has never seen a foam roller and is wondering what I am talking about, this is what one looks like...

 
As you can see, they aren’t flash and they aren’t fancy. 


You might be wondering why this piece of foam is so special?  


Why should I use one?

Most athletes will use a foam roller with the aim to reduce muscle soreness and enhance their recovery in order to maximize their levels of performance.  But how is this achieved?


What do they do?

In simple terms, just think of foam rolling as ironing (stay with me).

When you train hard, muscles suffer from micro trauma. This micro trauma can lead to the formation of scar tissue and knots in the muscle, which may impede nerve conduction and blood flow. This can then lead to muscle soreness and reduce the contraction speed of your muscles, therefore your performance!

By carefully aligning the roller with particular muscles (like an iron), the roller is used to apply pressure to areas of soreness in muscles. This enables you to break up the scar tissue that may have formed (like creases in a shirt).


They can also be used to increase your flexibility and your range of movement, a process called autogenic inhibition. As pressure is applied to the muscle, mechanoreceptors called Golgi Tendon Organs inform the brain that tension is being placed on the muscle. The brain then sends a message back to relax the muscle, preventing it from tearing.  A reduction in tension means a reduction in pain and improvements in muscular function.


How do I use one?

As briefly mentioned, rollers are used to apply pressure on areas of soreness in your muscles. They are really simple to use. Place the roller on a sore muscle area and roll slowly, using your body weight to apply the pressure. Once you have found a sore point, stop and apply direct pressure whilst trying to relax the muscle. It is advised to spend between 30-60 seconds per muscle group, depending on your perceived soreness.


Foam rolling is a great method to use as part of a pre-hab routine before your training session or as part of a recovery routine after your session. It becomes a great habit to have in making sure that you are getting the most out of your training sessions.


But does it actually work?


What does the research say?
 
There are many studies that have researched the effectiveness of foam rolling but I have summarised the findings of two recent papers. The references can be found below in case you would like to look into them further.


The first paper looked at was by MacDonald et al. (2014). This study looked at foam rolling as a recovery tool after an intense bout of physical activity. Results concluded that foam rolling was a beneficial tool in reducing muscle soreness whilst also improving vertical jump height, muscle activation and passive and dynamic range of motion in comparison to a group that did not use foam rollers.

A study by Pearcey et al. (2014) found results that adhered to the findings by Macdonald et al. (2014). They concluded that foam-rolling effectively reduced the delayed onset of muscle soreness (DOMS) and the associated decrements in dynamic performance (sprint speed, power and dynamic strength endurance).

So that’s a little bit about self-myofascial release; why not get your hands on a foam roller and try it for yourself. I’d love to hear what you think!


References

Macdonald, G., Button, D., Drinkwater, E. and Behm, D. (2014). Foam Rolling as a Recovery Tool After an Intense Bout of Physical Activity. Medicine and Science in Sports and Exercise, 46 (1), pp.131-142.

Pearcey, G., Bradbury-Squires, D., Kawamoto, J., Drinkwater, E., Behm, D. and Button, D. (2014). Foam Rolling for Delayed-Onset Muscle Soreness and Recovery of Dynamic Performance Measures. Journal of Athletic Training. [In Press]


This article was written by Rob Etherington.

Friday, 28 November 2014

Can't Do Pull Ups? We Have 7 Tips to Get You There

Pull ups are a basic movement in CrossFit, yet in and of themselves they are an intermediate gymnastic movement. Starting out pulling your bodyweight can seem like an insurmountable task.

Don’t fall prey to the mistakes of progressing too fast, kipping before you’re ready, or skipping over the fundamentals. There are tons of strategies and methods of assistance to get your chin over that bar, but not all of them are helping you to get stronger.

Here we will learn where to begin and which alternatives are worth your time. Here are seven tips for achieving that beautiful, dead-hang pull up:

1. Work Your Mobility

Pullups begin as all movements do - with proper mobility. Work on being able to maintain a proper overhead position exactly as described in my article The Safest and Smartest Progression for Building Your Overhead Lifts. If you start with tight lats, chest, or spine you’re already in a compromised position. This will put more stress on your shoulder joint and spine. For a pull up, you must start in a deadhang position with active shoulders. Once you can hang in this position in a controlled manner, then you can start pulling motions.

If you are unable to achieve a proper active hang position, you can still start building strength while working on your mobility. Work on grip strength using heavy deadlifts along with farmer’s carries. Both will stress the forearm and hands in a similar way to a pull up. To begin building pulling strength, you can do bent over barbell or dumbbell rows. Both are effective at building pulling strength and require less mobility to perform correctly.

2. Get Some Hang Time

Once you open up the mobility to dead hang properly, then you need to start spending time on the bar. Dead hangs for time are an effective way to build shoulder stability and grip strength. Make sure you never let your form suffer during these.

3. Avoid Jumping and Rubber Bands

Jumping pullups and banded pullups are popular in the CrossFit world as a way to get in a workout, but I’ve found little success with these methods and little direct translation into actual pull up strength. Strict banded pullups can be decent for building strength, but during a metcon they get abused and people begin to kip, bounce out of the hole, and squirm in all sorts of ways to finish their reps. If you’re after metabolic conditioning, switch to rows, deadlifts, rowing, ring rows, or some other variation.

4. Build Strength

To get your first pullup what you want to do is build strength. This means operating at 80%+ of your max effort at a minimum. Ring rows are one of the most effective methods to build strength and are easily varied in intensity by changing your positioning. Mark your foot positioning each workout and begin to creep your body closer to parallel with the floor each time. This will increase the load by involving a greater percentage of your bodyweight.

Negative pullups are also effective at building strength. Start with a five-second controlled descent and build to longer durations of time. Eccentric work can be very taxing and leave you sore, so start conservatively and add on as your body tells you. Don’t combine a lot of eccentric pulling work and then a hard metcon involving similar movements.


5. Stay Focused

Remember the body can adapt well in one way at a time. It’s hard to increase strength and endurance at the same time. This is why we cycle our training and have times when we focus on strength and times when we focus on conditioning. If your goal is to do a pull up, then focus on getting that first one now, and then multiple reps later.

6. Resist the Kip

Don’t kip until you can do at least five strict pullups. Kipping is the translation of horizontal momentum to vertical force and allows you to do a greater number of pull ups. Kipping is more efficient, but it also loads the shoulder dynamically, putting more force on it. If you are unable to control your bodyweight, there is no reason to add momentum on top of that.

7. Climb a Rope

Another movement great at building pulling strength is rope climbs. Rope climbing with efficiency involves using your legs to hook the rope and push yourself higher. Your arms hold you in place as you bring your legs up. So for a rope climb you only need to be able to hang on, not just pull your way to the top. Therefore, this is a great tool for people still working on building their pulling strength. If you’re a beginner, though, remember to let your legs help you so you don’t just focus on your arms and get burned out.

Respecting the pullup, training for your current ability level, and listening to your body will yield long-term results. If you’ve never done a pull up, then it’ll take time to get there, but the long smooth road always beats the ups and down of overtraining and progressing too quickly.

Thursday, 27 November 2014

3 Simple Ways to Heal a Stiff, Sore, or Injured Neck

Now, we are going to focus on cervical strain and give you some simple ways you can help yourself heal.

Cervical Strain or Sprain

In the case of a cervical strain/sprain, there are a number of things that can be done to facilitate healing. As a licensed acupuncturist I have been trained in numerous treatments and protocols to help this condition, but I wanted to pick techniques that wouldn’t require any special knowledge or training to do. These three therapeutic techniques are intended to be used after the acute-phase of the injury, which is the first four days after the incident.

Remember that after a neck strain/sprain, the muscles in the neck will often become tight, guarding the affected area and limiting motion and mobility.Anything that can be done to safely alleviate muscle tension, improve range of motion, and promote blood circulation to the affected area, is going to help the healing process.

A. Manual Cervical Traction

cervical spine, cervical injury, neck injury, bjj injuryApplying gentle traction to the neck can often ease and elongate tight muscles, allowing pinched nerves or compressed blood vessels to be released.

Tight muscles will constrict and compress everything around them. The idea behind using traction is to create more space and alleviate pressure by improving the blood supply to the neck muscles, tendons, and ligaments of the affected area.

One of the simplest ways to do this is to:
  1. Lie down on your back and place a folded (lengthwise) hand towel under the occiput of your head. This is the rear part of your skull that rounds out away from your neck.
  2. Have a friend gently pull the towel straight towards them. Try to get them to hold the position for at least 3 minutes.
  3. Repeat the exercise 2-3 times per-day or until you feel some relief. I have seen excellent results in my own clinic with as little as a few minutes a day.


B. Hydrotherapy

Soaking in Epsom Salt can be very helpful for the release of muscle aches and pain. It is informative to remember the actual name of Epsom Salt is Magnesium Sulfate. Among magnesium’s many functions is it will reduce the rate of calcium binding after a muscle contracts as it competes for the same binding sites as calcium, which contracts a muscle.

Something as simple as an Epsom Salt bath can be of great benefit in relaxing a tight muscle.

It is easily done by
  1. Adding 2 cups of Epsom Salt to a warm bath full of water.
  2. Soak your neck in the bath for 15 - 20 minutes, allowing the Magnesium to be absorbed through your skin.

C. Acupressure Point for Stiff Neck

Luo Zhen is the name of an acupuncture/acupressure point used specifically for a stiff neck. The point is found on the back of the hand in between the two bones in the depression just past the knuckles of the pointer and middle finger.

How to use Luo Zhen to treat a stiff neck:
  1. Massage the point on the opposite side of the body from the neck pain. If the right side of your neck hurts, massage the point on your left hand. You will need to massage this point by pressing into it with the tip of your finger, and make sure to use enough pressure to feel slight tenderness at the point.
  2. Maintain that pressure while making very small circles with your pressing finger.
  3. At the same time as you are stimulating the acupressure point, exercise the neck by rotating your head side to side. You should slowly begin to notice a slight increase in your range of motion while experiencing a decrease in pain.

cervical spine, cervical injury, neck injury, bjj injury, luo zhenOnce, I treated an elderly woman with severe neck pain and limited range of motion from sleeping in a bad position.

I tried using the acupuncture point Luo Zhen for several minutes while she exercised her neck. To my surprise, there was no result or improvement at all.

Rather than give up, I decided to try again. This time I worked on the point for more than ten minutes and then rechecked. She had a very slight increase in her range of motion. After forty minutes of treatment we had the full mobility of her neck restored and no pain.

Patience and Persistence Are Important When Treating Neck Pain

I’m not telling this story to say that everyone is going to have these types of miraculous results with this or any of the other techniques. What I want to point out is sometimes it will take some patience and the ability to acknowledge even a small amount of progress in order to fully restore one's health. Had I just given up after my first attempt, the treatment may not of had any benefit at all.

Do you have a sore neck? Give one of these treatments a try and post your results to the comments below.

Monday, 24 November 2014

Why Do We Get Injured? And Can It Be Prevented?

My Story

I’m lying on my side with an oxygen mask over my mouth. The anaesthetist is sitting next to me. It seems to take an age for me to understand what he is saying; “Can you feel that? Does it hurt?” In my head, I slowly register his words through the fog of sedation. It does hurt; it hurts a lot. And it would hurt – after using a hammer to insert a metal tube into my spine, my surgeon is now using a saw to cut out bits of my disc. I’m kept awake so that I can move my leg if required, which is an important step to make sure I’m not suffering any permanent nerve damage. Although sedated, I can feel pain. Fortunately, my anaesthetist can turn up the sedation and put me to sleep, putting a temporary end to it all. After three hours of surgery (which was supposed to only last 45 minutes), I am wheeled into the recovery room to wake up fully. This is where the most painful experience of the whole operation occurs. All the deep tissue that lies around the spine, which has been in spasm for three months to protect the area of instability, suddenly realises it can relax a bit. All the toxins and waste products that have been building up in the tissue are released, and an intense feeling of pain hits me in my lower abdomen, which lasts for about 15 minutes, until the pain killers administered by the nurse kick in.
Damaged Disc
Figure 1: Disc that was removed during surgery.

So, how did I get to this point? I suffered my first real back injury when I was 18. Although I didn’t have an MRI scan on that occasion, judging by the symptoms I experienced, I was probably suffering from a disc issue. Then, when I was 20, it came back again. My back would seize up from time to time, making any activity difficult for a few days. It had a nasty habit of doing so in warm-ups for races, which made running difficult. This time, I did have an MRI scan, which showed dehydrated discs and a few protrusions in my lumbar spine. A plan was devised to work our way round this problem, and I managed well, suffering no real back symptoms after that year for the following three competitive seasons.
Then, in 2011, I was in the gym doing deadlifts. I’d love to say I was lifting a heavy weight, but the truth is I wasn’t – it was only about 60% of my rep maximum. About halfway through the set, I lifted the weight from the floor, and as I did, I remembered thinking that my back position wasn’t quite right. As soon as I thought this, I felt a weird shift in my back, like something moving backwards, followed by a shot of pain at that specific site, which then transformed into a very global, very severe pain. Every single muscle, from my knees to my neck, had spasmed. The spasm on my right side was so great that it pulled my pelvis towards that side, which made walking pretty hard. An MRI scan showed a pretty severe disc bulge in one of my troublesome lumbar discs. I rehabilitated for the next 12 weeks, got back into some decent running, and managed to run 10.19 that season.
Off the back of this 2011 season, I was all ready to go to the 2012 Olympics, which were taking place in my home country. I had been looking forward to this for ages, had moved to a place and a training group I thought could enable me to do this, and had just had a reasonably successful season despite missing a lot of training due to my back. I can’t remember the exact day I started to feel pain in my right hip, but it was around the start of November. I had another MRI, which showed that one of my discs had further degenerated, and would probably require surgery in about five years. As November turned into December, my symptoms were slowly getting worse; I’d wake up in the night and not be able to feel my right foot. I wouldn’t be able to lift my right leg high enough when running—all classic signs of reasonably severe disc dysfunction. But, because I wanted more than anything to qualify for the Olympics, I pushed it to the back of my mind. Another MRI in December showed that I would probably need surgery after the Olympics; that was fine by me as long as I could get there. At the end of December, I had an epidural and some injections in my back to settle down the symptoms and traveled to South Africa for a warm weather training camp. On the fifth day there, I woke up one morning, unable to move. There was no acute incident; I only went to sleep one night, and I woke up a wreck. I knew then that this was very, very bad. I didn’t train for the rest of the camp; I flew home and saw the surgeon, who recommended surgery. My MRI now showed a herniated disc severely impinging on my sciatic nerve. My surgery was set up for two months later. Living through those two months was tough; because my sciatic nerve was affected to such a degree, I was comfortable only in two positions, exactly straight (standing or lying) and exactly on my left side. Every other position caused excruciating pain and pressure in my leg. If I wanted to sneeze (when I had a cold), I used to have to stand in a doorway, brace my body and head against the door frame, and sneeze there to prevent my head from jerking forward, which was agony.
Fortunately, my surgery went well, and I ended up with about 50% of my L3-4 disc getting removed. I slowly rehabilitated myself, switched to bobsleigh, and got selected for the Winter Olympics. Sadly, once I was there, my back injury flared up again, and I was forced to withdraw and retire.

Why do we get injured?

If you are reading this and have taken part in sports at any level, you will have suffered a sporting injury. My back injury was on the severe end of the spectrum, but injury is something we all have to deal with. There are two types of injury: chronic and acute. An acute injury is a sudden onset, and the inciting event is identified by the application of some external force (Meeuwisse 1994). A chronic injury is an overuse injury, where repetitive micro trauma eventually causes an injury. But why do we get injured? Bahr and Krosshaug (2005) developed the “Comprehensive model for injury causation,” and, as the title suggests, it is very comprehensive! For an injury to happen, they state that there is an inciting event on a susceptible athlete. The more susceptible the athlete, or the more severe the inciting event, the greater the chance of injury.
Internal Risk Factors
Bahr and Krosshaug identified the following internal risk factors that make an athlete predisposed to injury:
  1. Age (maturation, aging)
  2. Gender
  3. Body composition (weight, fat mass, anthropometrics, bone mineral density)
  4. Health (history of previous injury, joint instability)
  5. Physical Fitness (strength, power, resistance to fatigue, joint ROM)
  6. Anatomy
  7. Skill Level (technique, postural stability)
  8. Psychological factors (competitiveness, motivation, perception of risk).
How well athletes score in these regions depends on how susceptible they are to injury. Take gender, for example. Being a woman significantly increases your chances of suffering anterior cruciate ligament injury (Arendt and Dick, 1995), potentially due to increased femoral tilt.
Interestingly, recent research has shown that our genetics can increase our predisposition to certain injuries. For example, a specific variant of the COL5A1 gene is associated with chronic Achilles tendinopathy (September et al., 2009).
Take my back injury as an example. I was at a massive risk of injury at that point of my career. I was genetically predispositioned to suffer from a back injury due to a syndrome I have, which means I have enlarged transverse processes, reducing my flexion and extension range, which, in turn, puts more pressure on my discs. (I’ve also recently had a DNA test done, in which I scored off the chart for injury risk!) I had a lot of previous injury in this area, which is an additional risk factor. My previous injuries had probably affected my movement patterning, which meant I wasn’t strong enough in certain movements, placing my already at-risk back in further likelihood of injury.

Exposure to extrinsic factors

Once an athlete with a high injury predisposition is exposed to external risk factors, the chance for injury is further increased. The external risk factors include sports factors, such as rules, protective equipment, and the environment. Within track and field, examples include a high training volume on a hard running surface potentially increasing the risk of shin injuries in athletes, or training outside in cold temperatures potentially increasing the chance of a musculoskeletal injury.
Using bobsleigh as an example, the environment in which the sport takes part is usually cold (I recall competing in -27 degrees Celsius), which increases the chance of musculoskeletal injury. There is also the possibility of injury from crashing, either an impact injury against the bobsleigh or track, or an ice burn from being held against the ice whilst being upside-down, travelling at 80 miles per hour. To reduce the risk of injury, we wear helmets and burns vests and strengthen our exposed areas to be able to handle the impact better.

Inciting Event

When we have a susceptible athlete who then comes into contact with an inciting event, then we have an injury risk. An inciting event could be a game-based situation, such as contact with another player or object, or falling over. It could be down to a biomechanical issue, such as a player changing direction and injuring his or her knee. In the case of a chronic injury, the inciting event could occur over a long period, eventually causing injury.
The inciting event for the injury that caused me to retire was pulling the brakes in the back of a bobsleigh. Pulling the brakes is a loaded spinal extension exercise, going from a position of sustained maximal spinal flexion to extension whilst pulling a load. I was already a severely at-risk athlete, taking part in an activity that exposed to me significant external risk factors (early morning activity, cold weather, technical requirements of maintaining extreme spinal flexion), which meant the chance of an inciting event was high. Had it not happened at that particular time, on that particular day, I strongly believe it would have happened at some point close to that, due to the fact that both the intrinsic and extrinsic risk factors were so great.

Can we predict an injury?

Once we know why we get injured, it would be useful to know if we can predict the chances of us getting injured. There is some evidence that we can. Obviously, every single athlete is predisposed to injury in some way through the mix of intrinsic and extrinsic factors, but there are ways we can predict who is more likely to be injured. The first is through a screening process. Gray Cook developed the Functional Movement Screen (FMS), which assesses athlete’s competencies at a variety of movements. Athletes that score poorly on the test are thought to be at more risk of injury. The jury is still out on the usefulness of screens such as the FMS. Kiesel et al. (2007) used the FMS in pre-season training with a football team and found that those that scored poorly were more likely to report an injury over the playing season. Freckleton et al. (2014) tested single leg hip bridging in a group of Australian Rules Football players in their preseason. The players that showed one leg to be significantly weaker than the other were much more likely to injure the hamstring in the weaker leg over the course of the season. Although it is still early days, genetic testing might be useful to give a picture of injury risk. Collins and Raleigh (2009) found that there is a wide variety of genes potentially associated with musculoskeletal injury. The ability to test genetics and use movement screens is potentially a really useful way to create effective training programmes to lower the injury risk.
Periods of high intensity or high volume of training are also a potential point of injury. Hullin et al. (2014) found that large increases in workload in a group of elite cricket fast bowlers were a reliable indicator of increased injury risk.
Poor nutritional status is also a risk factor for injury. Athletes that are in energy deficit are more likely to be in a fatigued state (as their recovery is potentially compromised) and so are at an increased injury risk. Various micronutrients also play a role in injury, including calcium and magnesium in bone health. Low levels of vitamin D have been linked to a decrease in bone mineral density as well the loss of muscle strength (Cannell et al., 2009). Athletes are generally vitamin D deficient, and so this is an easily modifiable risk factor.

How do we reduce our chances of getting injured?

Boxing Protective Gear

Figure 2: Boxers wearing gloves and protective headgear. WCAP boxers medal at U.S. National Championships – FMWRCby US Army

Is there anything we can do to prevent ourselves or our athletes from getting injured? In a recent meta-analysis on the effectiveness of injury prevention techniques, Lauersen et al. (2014) found that strength training is highly significant in reducing injuries. The mechanism for this is that the musculoskeletal system adapts to strength training, allowing the athlete to handle high loads more easily. Proprioceptive and co-ordination training were also shown to be helpful in reducing the injury risk. However, passive stretching pre-training or pre-competition does not show any protective effect. In my opinion, if a muscle is tight enough to restrict the range of motion at a joint, then this places you at an increased injury risk, and steps should be taken to address this. Chronic tightness in a muscle increases the chance of injury in that muscle through a variety of factors, and also potentially increases the global injury risk as it could cause other muscles to have to overwork.

Tips to Reduce Injury Risk

  • Consider a regular physical screening to assess current movement competencies, and pick up on any imbalances or strength deficits that may contribute to injury.
  • Ensure appropriate strength training is in place with adequate and sensible progressions for your age and maturation.
  • Make sure that your body composition is at the correct level for your sport. Being too heavy can increase the stress and force going through your joints, muscles, and ligaments. Some adipose tissue may be useful in contact sports to protect against impact.
  • Consider the sport specific demands of what you do, and ensure that your body can meet these demands. As a case in point, when I converted to bobsleigh, I had to ensure I could hold and maintain a large amount of spinal flexion in the back of the bobsleigh. To begin with, I couldn’t, but I designed a pre-habilitation programme to enable me to do this. Soccer players require greater conditioning of the ankles in order to handle cutting movements and also reduce the risk of ankle sprains in a tackle. An additional bobsleigh example of my own was the need to increase my neck strength so that if we ever crashed, I could use my head to lift my body off the ice, preventing ice burns. With regard to sprinting, the hamstrings have to be able to handle a large eccentric load throughout the sprint cycle, so they should be adequately conditioned to manage this task.
  • Try to avoid large, sudden increases in training volume or intensity. If these can’t be avoided, then ensure that appropriate recovery techniques are used.
  • Strive to meet the energy demands of your sport. Training and competing in a fatigued state increases the injury risk, so make sure you are conditioned enough to meet the demands.
  • Ensure that you have an adequate range of motion in the correct joints and that all areas are working well. If one joint has a less-than-adequate range of motion, it increases the chance of injury in that area and the pressure on the surrounding joints.
  • Fully recover from any previous injury. Keep rehabilitation going until there is no strength deficit in the muscle and normal motor patterning has returned.
  • Make sure your nutritional status is good; you should get sufficient vitamins and minerals to ensure that your bones and immune system are healthy.
  • Work on your posture and ability to hold this posture under fatigue. Being in the correct position at the correct time ensures optimal technique, which reduces injury risk. Being able to contract the right muscles at the right time is crucial to reduce injury risk. Let me illustrate this point: I currently suffer from right knee pain because my right gluteus medius has atrophied (due to nerve damage), so, under load, I can’t control my thigh as well as I used to in the past.
  • Make sure you aid your recovery from training. Sufficient sleep is important!
  • Improve your technique as much as possible. Poor technique is a risk factor for injury as it is usually less economical and can overload certain muscle groups.
This post was expertly written by former Team GB Olympic Sprinter, Craig Pickering.

What's Popular Now